
Attachment and Biobehavioral Catch-Up (ABC) is a brief, manualized parenting intervention for caregivers of infants and toddlers who have experienced early adversity, and it occupies a specific and useful niche for clinicians who work upstream of entrenched relational and regulatory difficulty. LLM This article orients practicing therapists to what ABC is, what it asks of the clinician, what the evidence does and does not support, and how to fold its mechanisms into recognized billable care.
Type & Discipline
ABC is a structured, time-limited, dyadic parent-coaching intervention rather than a child-directed psychotherapy. LLM It sits at the intersection of clinical and developmental psychology, drawing on developmental research that identified specific parenting deficits in caregivers of children exposed to early adversity. 6 Its target is the caregiver’s behavior in the moment with the child, on the premise that changing caregiving in turn changes the child’s attachment and biobehavioral self-regulation. 6 It is typically delivered as a brief course of roughly ten sessions in the family’s natural environment, most often the home. LLM2
Creators & Lineage
ABC was developed by Mary Dozier and her research team out of a program of work on the development of young children in foster care and young children living with neglecting birth parents, examining their challenges in attachment and regulatory capabilities. 4 Dozier holds the Unidel Amy E. duPont Chair in Child Development and is Professor of Psychological and Brain Sciences at the University of Delaware, where she was named Francis Alison Professor in 2016 and received the American Psychological Association’s Urie Bronfenbrenner Award in 2019. 5 She also serves as Executive Director of the ABC Parenting Institute, which supports training and dissemination. 5 The model’s intellectual lineage runs through attachment theory and developmental psychopathology, with a behavioral-coaching structure that parallels other dyadic parent-training models such as Parent-Child Interaction Therapy. LLM Several of the core ABC trials cited here were led with colleagues including Lindsay Zajac, K. Lee Raby, and Heather Yarger. 23
Core Principles
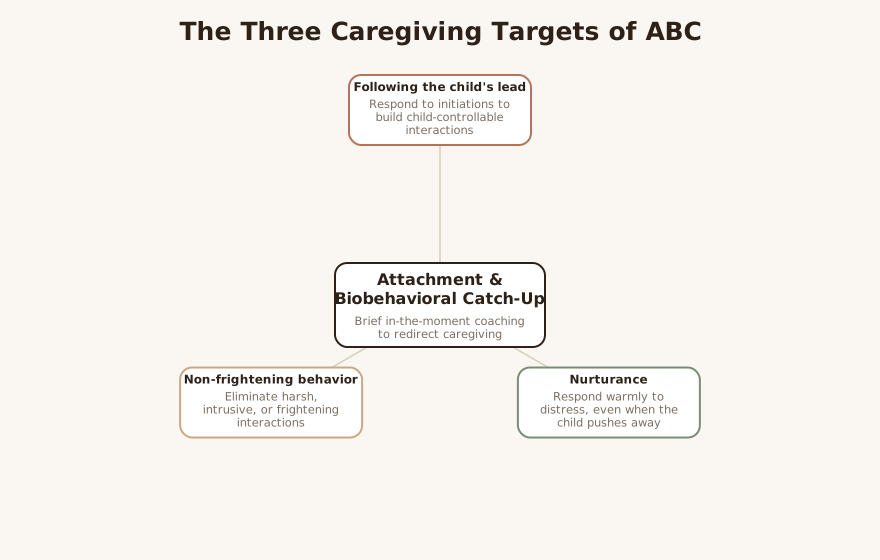
ABC organizes itself around three primary caregiving targets. 6 The first is following the child’s lead, in which the caregiver responds to and builds on the child’s initiations to create smooth, child-controllable interactions that scaffold behavioral and biological self-regulation. 6 The second is nurturance, the deliberate practice of responding warmly when a child is distressed, even when the child’s history of adversity has taught them to push caregivers away rather than signal need clearly. 6 The third is non-frightening behavior, helping caregivers recognize and eliminate harsh, intrusive, or frightening interactions that undermine regulation and contribute to disorganized attachment. 6 Underlying all three is the assumption that children’s biobehavioral systems, including stress physiology, are shaped by the quality of moment-to-moment caregiving and can be redirected toward more normative functioning. 6
Interventions & Techniques
The signature ABC technique is in-the-moment commenting. 6 Rather than teaching parenting skills didactically between interactions, the parent coach observes the live caregiver-child interaction and delivers real-time, specific, positive feedback the instant a target behavior occurs. 6 As Dozier describes it, parent coaches make comments that support parents following their children’s lead, naming the specific parenting behavior and linking it to the child’s response so that sensitivity compounds across the session. 6 This frequent, behaviorally precise narration is what distinguishes ABC from reflective or insight-oriented parent work. LLM Fidelity is monitored through review of brief weekly session clips, a system designed to preserve research-grade quality when the model is delivered in community settings. 6
LLM-generated illustrative example (not a guideline): A 14-month-old in foster care pushes a toy toward her foster mother, who picks it up and hands it back rather than redirecting to her own agenda. The coach immediately says, “There — she handed you the block and you took it and gave it right back. That’s you following her lead, and notice how she settled and looked at you.” The comment is concrete, tied to the child’s regulatory response, and delivered in the second it happens. LLM
Evidence Base
The evidence base for ABC is best characterized as established, with the caveat that strength varies by outcome and time horizon. LLM A systematic review identified ten articles reporting randomized controlled trials of ABC and concluded that, when implemented with child-welfare-involved children, ABC is effective at improving emotion regulation, reducing externalizing and internalizing difficulties, advancing developmental milestones, and strengthening attachment security; the review noted ABC’s designation as a high-level evidence-based practice for child welfare. 1 The strongest and most durable findings concern proximal relational outcomes: in a randomized clinical trial of 100 children referred to Child Protective Services, children whose parents received ABC showed higher attachment security on the Kerns Security Scale at age nine than control children, demonstrating that a brief ten-session infancy intervention can sustain attachment benefits across roughly an eight-year span. 2 Reported biobehavioral effects, including more normative cortisol patterns, come from the broader program of work and should be read as reported findings within that literature rather than as the primary endpoint of any single trial cited here. 6
Honesty requires noting that effects on some distal behavioral outcomes are more mixed and can fade. LLM In a randomized controlled trial of 122 internationally adopted children, parents receiving ABC reported fewer child behavior problems than a control condition from immediately post-intervention through 1.5 years later, and ABC children showed fewer regulation problems in parent contexts at 48 months — but no group differences emerged at 60 months or in examiner contexts. 3 The pattern suggests ABC’s effects are most robust for parental sensitivity and the caregiver-mediated outcomes closest to its mechanism, and weaker for outcomes more distal in time or context. LLM
Populations & Indications
ABC is indicated for infants and toddlers who have experienced early adversity and the caregivers who are raising them. 6 Core populations include foster children, adoptive families (including children adopted internationally, many of whom experienced prior institutional care), and maltreated or neglected children. 36 It was developed specifically for high-risk caregivers and child-welfare-involved families, including birth parents at risk of neglect and CPS-referred dyads. 24 The intervention is developmentally targeted to the infant and toddler window, when caregiving has its most direct leverage on emerging attachment and regulatory systems. 6
Problems-for-Work
ABC is well matched to the relational and regulatory problems that follow early adversity. LLM For disorganized and insecure attachment, the nurturance and non-frightening targets directly address the caregiving patterns implicated in disorganization. 6 For child maltreatment and early childhood trauma, ABC functions as a relational repair and prevention intervention delivered to the caregiving system. 1 For emotional and behavioral dysregulation, following the lead scaffolds the child’s capacity to self-regulate during interaction. 6 For cortisol and stress-regulation problems, the model targets the caregiving inputs reported to shift children toward more normative stress physiology. 6 For parent-child relational problems, in-the-moment commenting builds caregiver sensitivity that improves attachment security measurable years later. 2
LLM-generated illustrative example (not a guideline): A clinician receives a referral for an 18-month-old in kinship care presenting with flat affect, minimal bids for comfort, and a foster grandmother who reads the child as “independent” and “fine.” The problem-for-work is a nascent insecure/avoidant pattern; ABC’s nurturance target would focus on coaching the caregiver to override the child’s misleading “I’m fine” cues and respond as if the child needs comfort. LLM
Contraindications, Cautions & Cultural Humility
ABC is a coaching intervention, not a crisis or safety intervention, and it presupposes that the child is in a caregiving placement where building the relationship is appropriate and safe. LLM Where active maltreatment, unaddressed caregiver substance use, or acute safety risk is present, child-protection and stabilization processes take precedence and should run in coordination with, not instead of, relational work. LLM Clinicians should hold the model’s targets with cultural humility: notions of “following the lead,” appropriate nurturance, and acceptable caregiver behavior are expressed differently across cultures, and in-the-moment commenting must affirm a family’s own warmth practices rather than impose a single normative template. LLM Fidelity monitoring helps standardize delivery, but it does not substitute for the clinician’s judgment about cultural fit and family context. LLM
Treatment-Plan Suggestions & SMART Objectives
| Goal | SMART objective (example) | Mechanism |
|---|---|---|
| Increase caregiver nurturance toward distressed child | Caregiver responds with physical/verbal comfort to ≥80% of child distress cues observed across 3 consecutive sessions | Nurturance target reduces disorganized attachment 6 |
| Increase synchrony / following the lead | Caregiver follows child’s initiation within 5 seconds in ≥70% of coded play bids over 2 sessions | Following the lead scaffolds self-regulation 6 |
| Reduce frightening/intrusive caregiver behavior | Eliminate observed harsh or intrusive episodes to 0 per session by session 6 | Non-frightening behavior supports secure attachment 6 |
| Improve child behavioral regulation | Caregiver-reported behavior-problem score drops to non-clinical range and holds for 6 months | Sensitivity gains reduce behavior problems 3 |
| Strengthen attachment security | Dyad shows secure-base behaviors on a structured observation by end of course | Coaching builds durable attachment security 2 |
| Improve caregiver in-the-moment responsiveness | Caregiver verbalizes child-led narration in ≥3 instances per session without prompting by session 8 | In-the-moment commenting internalized 6 |
| Support more normative stress regulation | Reduce caregiver-reported child distress-recovery time by half over the course | Caregiving inputs linked to cortisol normalization 6 |
The table cells above are illustrative planning examples, not validated benchmarks, and clinicians should set thresholds to the individual dyad. LLM
Common Misconceptions
A frequent misconception is that ABC is a long-term psychotherapy; it is a brief, roughly ten-session model. 2 Another is that it works directly on the child — its mechanism is the caregiver’s in-the-moment behavior, with child outcomes following from changed caregiving. 6 Clinicians sometimes assume ABC teaches parenting through instruction or homework, when its distinctive ingredient is live, second-by-second positive commenting during real interaction. 6 A final misconception is that strong attachment findings imply equally strong, lasting effects on every behavioral outcome; the international-adoption trial shows some behavioral effects fade over time and do not generalize to all contexts. 3
Training & Certification
ABC is a manualized model with structured training and fidelity supervision rather than a technique a clinician can adopt from reading alone. LLM Training and dissemination are supported through the ABC Parenting Institute, which Dozier directs. 5 Quality is maintained in practice through ongoing fidelity monitoring, including review of brief weekly session clips to keep community delivery aligned with the research protocol. 6 Clinicians interested in delivering ABC should pursue the formal training pathway rather than improvising the model’s coaching structure. LLM
Key Terms
Following the lead — responding to and building on the child’s initiations to create smooth, child-controllable interactions that support self-regulation. 6 Nurturance — warm, comforting responses to a child’s distress, practiced even when the child’s history suppresses clear bids for care. 6 Non-frightening behavior — the absence of harsh, intrusive, or frightening caregiver behavior that would undermine regulation and secure attachment. 6 In-the-moment commenting — the coach’s real-time, specific, positive feedback delivered as target caregiving behaviors occur. 6 Attachment security — the child’s confidence in the caregiver as a secure base, here measured years later via the Kerns Security Scale. 2 Biobehavioral regulation — the coordinated behavioral and physiological (e.g., cortisol) self-regulation systems that early caregiving shapes. 6
Resources & Further Reading
▶ Watch — a video introduction to this concept:
- Grube & Liming (2018), Attachment and Biobehavioral Catch-Up: A Systematic Review
- Zajac, Raby & Dozier (2020), Sustained effects on attachment security in middle childhood — RCT of ABC
- Yarger et al. (2022), Intervening with ABC to Reduce Behavior Problems Among Children Adopted Internationally — RCT
- Mary Dozier — University of Delaware faculty profile (Infant Caregiver Project)
- Mary Dozier — ABC Parenting Institute
- The Attachment and Biobehavioral Catch-Up (ABC) Intervention — APA Division 7
- ABC – Infant — HomVEE (Home Visiting Evidence of Effectiveness)
- ABC Intervention — Dr. Mary Dozier (full video)
Reflective / Supervision Questions
- When you watch a dyad, how quickly and specifically can you name a caregiver’s nurturance or following-the-lead behavior in the moment, and what gets in the way of commenting in real time? LLM
- A caregiver reads a child’s avoidant “I’m fine” cues as genuine independence; how would you coach toward nurturance without shaming the caregiver’s interpretation? LLM
- Given that some ABC behavioral effects fade by 60 months and do not appear in all contexts, how will you set realistic expectations with families and referral sources? 3
- How do you adapt the three targets to a family’s cultural expression of warmth and discipline while preserving the model’s mechanism? LLM
- Where ABC is not separately reimbursable, how will you document the relational coaching within a recognized billable modality without distorting the clinical work? LLM