
Type & Discipline
Game theory is a branch of mathematics and economics concerned with the formal analysis of strategic decision-making among two or more interdependent agents, where each agent’s best choice depends on what the others choose 1. It is not a psychotherapy, a clinical model, or a treatment protocol LLM. Within game theory, the Nash equilibrium is a central solution concept: an outcome in a noncooperative game in which no player’s expected outcome can be improved by changing only their own strategy 1. The framework’s relevance for clinicians is as a conceptual lens, a vocabulary for describing how people behave when their interests are partly aligned and partly opposed, rather than as a billable intervention in itself LLM.
The reason it earns a place in a clinical wiki is that so much of relational and family work is, structurally, a problem of interdependence: each party’s behavior is rational given their expectations of the other, even when the joint result is poor LLM. Game theory gives that intuition a precise, teachable shape LLM.
Creators & Lineage
The modern field was founded by mathematician John von Neumann and economist Oskar Morgenstern in their 1944 book Theory of Games and Economic Behavior, described by its publisher as “the classic work upon which modern-day game theory is based” 4. Their work established a mathematical theory of economic and social organization built on a theory of games of strategy 4. A few years later, the mathematician John Nash extended the field beyond the two-person zero-sum cases von Neumann had emphasized, defining the equilibrium that now bears his name; he was awarded the 1994 Nobel Prize in Economics for his contributions to game theory 1.
The lineage that connects game theory to clinical practice runs through the social sciences rather than the mathematics LLM. Social exchange theory in social psychology and sociology borrowed the language of costs, rewards, and payoffs to model relationships LLM. Behavioral economics later complicated the assumption of perfectly rational, self-interested players, showing how cognition, emotion, and bias shape real choices LLM. And systems theory, foundational to family therapy, shares game theory’s core insight that you cannot understand one member’s behavior without understanding the interlocking responses of the others LLM.
Core Principles
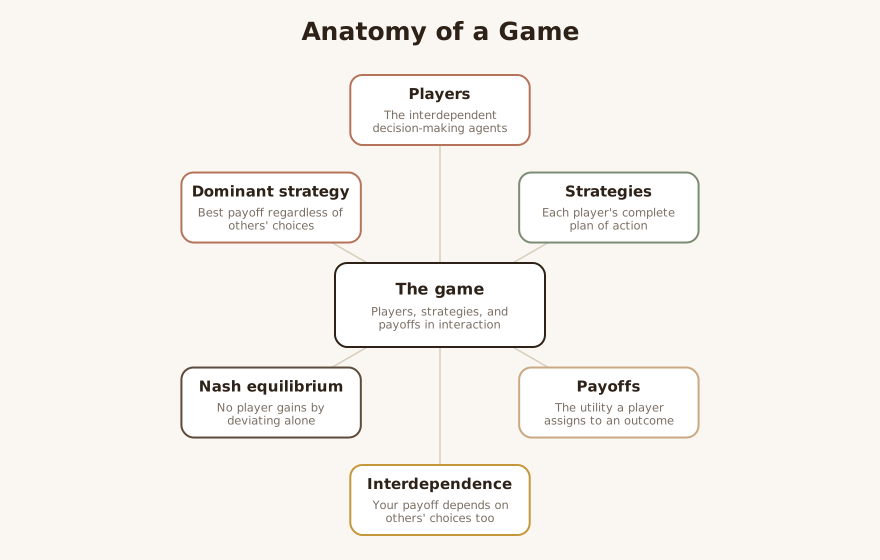
A game in this framework is any situation with players, the strategies available to each, and the payoffs each receives depending on the combination of strategies chosen 5. A strategy is a complete plan of action; a payoff is the value (utility) a player assigns to a given outcome 2. The defining assumption is interdependence: a player’s payoff depends not only on their own choice but on the choices of others 6.
The Nash equilibrium is the framework’s anchor. Formally, it is a strategy profile in which each player’s strategy is a best response to the strategies of the others, so that no player can gain by unilaterally deviating 2. Put plainly, it is a stable resting point: given what everyone else is doing, no individual has an incentive to change 3. Crucially, an equilibrium need not be good for anyone; it is merely self-enforcing 3.
A dominant strategy is one that yields a better payoff regardless of what others do; when each player has one, their intersection is an equilibrium 6. Games can be cooperative (binding agreements are possible) or noncooperative (they are not), and the Nash equilibrium belongs to the noncooperative world, where players cannot rely on enforceable promises 1. The Britannica treatment notes a clinically resonant point: communication between participants “can drastically alter their best strategy” 1.
The single most quoted illustration is the prisoner’s dilemma, in which two accused prisoners each decide whether to confess 1. The Nash equilibrium is mutual confession, even though both would do better by staying silent, because from each prisoner’s isolated standpoint, confessing is the safer choice 1. The collectively optimal outcome and the equilibrium outcome diverge, and the equilibrium is the one that holds 1. This gap, between what is individually rational and what is jointly best, is the bridge to clinical work LLM.
Interventions & Techniques
Game theory supplies no techniques of its own; in the consulting room it functions as a framing and psychoeducation tool inside a recognized therapy LLM. Several adaptations recur in practice LLM.
The first is naming the structure. A therapist can help a couple or coparenting pair see that their stalemate has the shape of a prisoner’s dilemma: each withholds cooperation because they expect the other to exploit them, and the mutual withholding is exactly the trap LLM. Drawing a simple two-by-two payoff grid on a whiteboard externalizes the conflict, moving it from “you are the problem” to “we are caught in a structure” LLM.
A second technique leverages the difference between one-shot and repeated games. The prisoner’s dilemma is bleak as a single encounter, but in repeated interaction, cooperation becomes rational because defection invites retaliation and trust pays off over time 3. Relationships are repeated games, and reframing them as such can motivate the patience that makes cooperation worthwhile LLM.
A third is shifting from noncooperative to cooperative framing. Because the dismal equilibrium depends on the absence of binding agreements and communication, interventions that build communication and credible commitment, the substance of most couples and family work, can move partners off the bad equilibrium LLM. The clinician’s role becomes helping the parties construct the enforceable, trusted agreements the abstract game assumes they lack LLM.
LLM-generated illustrative example (not a guideline): A divorced coparenting pair each unilaterally undercut the other’s household rules, reasoning, “if I hold the line and they don’t, our child just learns my house is the strict one.” On a whiteboard the therapist maps the four cells: both enforce, neither enforces, and the two mixed cells. The pair recognize that their current pattern, mutual non-enforcement, is the worst joint cell, chosen only because each fears being the “sucker.” The conversation shifts toward a written, mutually monitored agreement, the credible commitment the bad equilibrium lacked LLM.
Evidence Base
Honesty about maturity requires separating two very different claims LLM. As a formal mathematical theory, game theory and the Nash equilibrium are fully established: the existence of equilibria in broad classes of games is a proven result, the founding texts are decades old, and the field has been recognized at the highest level, including the 1994 Nobel Prize in Economics 14. There is no live debate about whether the mathematics works 2.
As a clinical intervention, the picture is entirely different LLM. There is no established body of randomized controlled trials, no manualized protocol, and no outcome literature validating “game theory therapy” as a treatment for any condition LLM. None of the foundational sources are clinical; they are mathematical, economic, and educational 123456. What clinicians use is the theory’s explanatory power as a metaphor and psychoeducation device delivered within evidence-based modalities LLM. So the correct summary is twofold: the framework is mature and rigorous, and its therapeutic application is analogical and unvalidated as a standalone treatment LLM. Clinicians should present it to patients in that spirit, as a useful map, not a proven cure LLM.
Populations & Indications
Game-theoretic framing is most apt where outcomes are genuinely interdependent and at least partly competitive LLM. Couples are the paradigm case, since most relationship conflicts are mixed-motive situations with shared and opposed interests LLM. Families and coparenting partners fit for the same reason, with the added complication of more than two players and asymmetric power LLM. Negotiating parties, organizations and teams, and groups in conflict map naturally onto bargaining and coordination games, making the lens useful in organizational consultation, mediation-adjacent work, and team coaching LLM.
The framing is indicated when a patient or dyad is stuck in a self-defeating pattern that persists despite everyone wanting a better result, the signature of a bad equilibrium LLM. It is less useful where the difficulty is intrapsychic, trauma-driven, or rooted in psychopathology rather than strategic interaction LLM.
Problems-for-Work
Relationship conflict and power struggles. Recurring fights often settle into a stable but miserable equilibrium that neither partner will break first; naming it as such reduces blame and opens negotiation LLM. A partner who “always gets the last word” can be reframed as locked into a dominant strategy that produces a poor joint payoff LLM.
Cooperation breakdown and mistrust. When one party stops cooperating, the other rationally follows, and the dyad slides to mutual defection LLM. Framing the relationship as a repeated game, where trust compounds and retaliation is costly, gives a rationale for risking the first cooperative move 3.
Coparenting conflict. Divergent household rules, undermining, and tit-for-tat retaliation map cleanly onto the prisoner’s dilemma, and the bad equilibrium is broken by building communication and credible, monitored agreements LLM.
Negotiation impasses and communication problems. Because the dismal equilibrium depends partly on the absence of communication, simply restoring credible dialogue can change each party’s best strategy 1.
Decision-making difficulties. For individuals facing interdependent choices, sketching the payoff structure clarifies which fears are driving a defensive, self-protective option LLM.
Contraindications, Cautions & Cultural Humility
The framing carries real risks if used naively LLM. Its language of payoffs, strategies, and self-interest can feel cold or accusatory, and it should never imply that a partner is “playing games” in the pejorative sense LLM. The theory assumes rational, utility-maximizing players, an assumption behavioral economics has shown to be only partly true of real people, so a clinician who treats the model as literal will misread emotion, attachment, and trauma as mere “irrational moves” LLM. It is contraindicated as a framing where there is intimate partner violence or coercive control: depicting an abusive dynamic as a symmetric “game” between equal players is clinically and ethically wrong, because the payoff structure is one of domination, not strategy LLM.
Cultural humility matters because what counts as a “payoff,” a cooperative move, or an acceptable outcome is shaped by culture, gender, family role, and power LLM. The Western, individualist premise of a self-interested rational actor does not map neatly onto collectivist or interdependent self-construals, where the relevant unit of utility may be the family rather than the individual LLM. Clinicians should let patients define their own payoffs rather than importing assumptions, and should hold the model loosely as one metaphor among many LLM.
Treatment-Plan Suggestions & SMART Objectives
| Goal | SMART objective (example) | Mechanism |
|---|---|---|
| Reduce blame-driven conflict | Within 4 sessions, the couple will jointly map one recurring conflict as a payoff grid and name the shared “bad equilibrium” in session without attributing fault | Externalizing the structure shifts attribution from person to pattern LLM |
| Restore cooperative behavior | Over 6 weeks, each partner will initiate one cooperative “first move” per week and track the other’s response | Repeated-game logic: cooperation compounds when retaliation is costly 3 |
| Rebuild trust after defection | Within 8 sessions, the dyad will draft one written, mutually monitored agreement and report adherence weekly | Credible commitment converts a noncooperative game toward a cooperative one 1 |
| Improve communication in impasses | By session 5, partners will hold one structured, time-limited dialogue per week before any decision | Communication “can drastically alter” each party’s best strategy 1 |
| De-escalate coparenting retaliation | Over 6 weeks, coparents will replace one tit-for-tat reaction with a pre-agreed response, logged between sessions | Breaking the defection cycle moves the pair off the worst joint cell LLM |
| Clarify a stuck individual decision | Within 2 sessions, the patient will sketch the interdependent payoffs of one decision and identify the fear driving the defensive option | Making the structure explicit reduces fear-driven, self-protective choices LLM |
| Increase insight into power struggles | By session 4, the patient will identify one “dominant strategy” they over-rely on and one cost it imposes on the relationship | Recognizing a dominant strategy reveals its poor joint payoff 6 |
Common Misconceptions
“Game theory is about manipulation or winning.” It is the formal study of interdependent choice; in mixed-motive games the rational result is often cooperation, and the equilibrium is frequently bad for everyone, the opposite of “winning” 1.
“A Nash equilibrium is the best outcome.” An equilibrium is only self-enforcing, not optimal; the prisoner’s dilemma’s equilibrium is worse for both players than the cooperative outcome 13.
“Players always reach the equilibrium because they are rational.” Real people are boundedly rational and emotionally driven; behavioral economics has repeatedly shown deviations from the idealized self-interested actor LLM.
“There is one equilibrium per game.” Many games have multiple Nash equilibria, which is precisely why coordination, communication, and credible commitment matter 3.
“It is an evidence-based therapy.” It is a mathematical framework borrowed as a metaphor; it has no clinical outcome evidence as a treatment LLM.
Training & Certification
There is no clinical certification in game theory, because it is not a licensed therapeutic modality LLM. Clinicians acquire it as background knowledge through introductory texts and courses in economics, mathematics, or decision science LLM. Martin Osborne’s An Introduction to Game Theory is a standard rigorous entry point, and its chapter on Nash equilibrium theory is freely available 2. The foundational source remains von Neumann and Morgenstern’s Theory of Games and Economic Behavior 4. Accessible nontechnical explainers, including those from Britannica, Built In, and the Corporate Finance Institute, are sufficient for the conceptual fluency a therapist needs to use the framing responsibly 156. The clinically meaningful “certification” is competence in the parent modality (couple, family, or cognitive behavioral therapy) within which the framing is delivered LLM.
Key Terms
Game: a strategic situation defined by players, available strategies, and payoffs 5. Player: a decision-making agent 2. Strategy: a complete plan of action for a player 2. Payoff: the utility a player receives from an outcome 2. Nash equilibrium: a strategy profile in which no player can improve by unilaterally deviating 12. Dominant strategy: a strategy that is best regardless of others’ choices 6. Prisoner’s dilemma: a game whose equilibrium (mutual defection) is worse for both players than cooperation 1. Cooperative vs. noncooperative game: whether binding, enforceable agreements are possible 1. Repeated game: an interaction played multiple times, where reputation and retaliation make cooperation rational 3. Zero-sum game: one player’s gain exactly equals another’s loss, the special case von Neumann emphasized 4.
Resources & Further Reading
▶ Watch — a video introduction to this concept:
- Nash equilibrium | Definition, Examples, & Facts (Encyclopaedia Britannica)
- Osborne, Nash Equilibrium: Theory (An Introduction to Game Theory, Ch. 2)
- Nash equilibrium (Wikipedia)
- von Neumann & Morgenstern, Theory of Games and Economic Behavior (Princeton University Press)
- An Introduction to the Nash Equilibrium in Game Theory (Built In)
- Nash Equilibrium - Game Theory Concept, Examples and Diagrams (Corporate Finance Institute)
Reflective / Supervision Questions
- When you introduce a payoff grid to a couple, are you externalizing the conflict, or subtly assigning blame through the language of “strategy”? LLM
- How do you know whether a stuck pattern is genuinely a strategic “bad equilibrium” versus a trauma-, attachment-, or psychopathology-driven dynamic that this lens would misread? LLM
- Whose definition of the “payoffs” are you using, the patients’ or your own culturally shaped assumptions about a good outcome? LLM
- Have you screened for coercive control or intimate partner violence before framing a dynamic as a symmetric game between equals? LLM
- Can you state, in plain language to a patient, that this is a useful metaphor rather than an evidence-based treatment, and notice when you are overclaiming? LLM
- Inside which recognized, billable modality are you delivering this framing, and are your documented goals tied to that modality rather than to game theory itself? LLM